Your Stroke / Brain Injury Recovery Starts Here


ARNI home-based training and guidance for your rehab is POWERFUL. Accept no substitute.

2026 marks 25 years of ARNI: Click Here to Claim your £50 off Full Set of Stroke Rehab 7 DVDs TODAY!

News

Researchers at the Technical University of Munich have built a soft, pneumatic glove that reads the intention to grasp from your forearm muscles and then closes your hand around the object. Published in Nature Machine Intelligence in June 2026 by John Nassour and colleagues, the ‘soft-hand exoskeleton’ is a fabric glove with air cushions on its outer surface, inflated through 13 small tubes that bend and straighten each finger individually and rotate the wrist… enough to hold a plate, or grasp a glass, fork or spoon. Sensors on the forearm pick up the electrical signals from your muscles (an electromyogram), and machine learning reads those signals to work out the movement you intend; the system then inflates the air cushions to support that exact movement.

Dr Nassour says the glove predicts grasping intentions from muscle signals with 97% reliability. To stop objects being dropped by accident, extra motion sensors detect when you are carrying something and hold the grip closed throughout the movement.The glove was developed with a patient who has amyotrophic lateral sclerosis (ALS), a condition in which the nerve cells controlling muscle gradually degenerate and is being designed to be transferable for stroke survivors, esp. those with flaccidity, later.

By the start of the project he had very little control of his hands but could still move the first thumb joint, so the researchers built the system around the strongest signals from his thumb muscles. Despite very weak signals, the glove recognised his intention in 9 out of 10 cases; he reached for objects, held a fork for the first time in four years, and picked up small cubes and dropped them into a container. A video game helped too… he had to make a character jump using only his thumb joint, and five minutes of this improved his ability to grasp considerably.

Two things stand out beyond the tech. The first is cost. Nassour sewed the glove himself, and the fabric costs very little; as institute director Prof Gordon Cheng puts it, ‘we’ve found a solution that anyone can afford but still works very well.’ Most upper-limb assistive robotics is expensive and confined to specialist centres, so a low-cost, home-viable device that works this reliably is unusual. The second is breadth. The team is now adapting the concept for other patients, including stroke survivors; neurologist Prof Tobias Wächter believes it can help people with flaccid paralysis more widely, including those with peripheral nerve damage from motorcycle or bicycle accidents, or patients with polyneuropathy.

This is obviously just early research, and the stroke version is still being developed rather than tested at scale – larger trials across different conditions and levels of impairment will be needed before anything reaches routine use. There is no UK availability, no regulatory approval and no confirmed timeline; realistically, routine use here is several years away. At ARNI, we work on grasp, grip and hand function from the earliest stages of recovery, and so an affordable device that reads your intention to move and then helps you complete it, at home, sounds very useful to us…

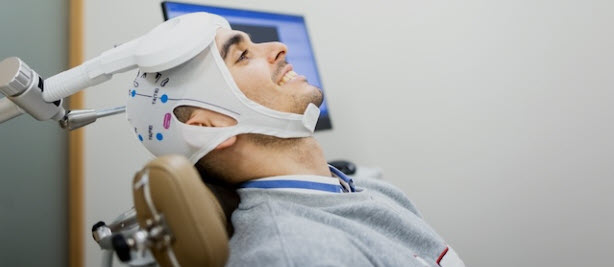
If you’ve come across transcranial magnetic stimulation (rTMS) as a possible (clinical) add-on to stroke rehabilitation, an interesting review published in July 2026 in the journal Brain Sciences, led by Marcin Karol Setlak and colleagues at the Medical University of Silesia in Poland, draws a careful line between what the tech can and cannot yet do. rTMS is a non-invasive way of changing the excitability of the brain’s motor and language networks; the idea is not to replace rehabilitation but to prime the affected area so that the physiotherapy or speech work you do afterwards lands more effectively. The review’s focus is a more precise version of it; neuronavigated rTMS (nrTMS)… which links the stimulation to your own MRI scan and tracks the coil position in real time.

So, conventional rTMS is usually aimed using scalp landmarks or standard coordinate systems, which give only a rough approximation of the cortical target underneath… and after a stroke, the lesion, the surrounding reorganisation and any change in brain shape can shift the relationship between the scalp and the region you want to stimulate. So two patients treated on the same nominal protocol can end up with stimulation over different targets. Neuronavigation reduces that uncertainty; the target is defined on the patient’s own MRI, the coil position and angle are monitored during stimulation, and the same target can be reproduced session after session. When rTMS is delivered over many sessions alongside motor training, that reproducibility matters, because small differences in coil placement otherwise add up.

Stroke is the most studied use of rTMS in rehabilitation, mostly for upper-limb motor recovery, but also for aphasia, neglect and dysphagia. Two broad strategies are common; low-frequency stimulation (around 1 Hz) to the undamaged hemisphere to reduce its inhibitory influence, or high-frequency stimulation to the damaged hemisphere to boost its activity. Both rest on the interhemispheric imbalance model, but the review is clear that neither should be applied mechanically… in patients with extensive damage to the corticospinal tract, boosting the lesioned side may not be enough, and in patients who rely on the other hemisphere for residual movement, suppressing it may do harm. Which strategy suits you depends on your lesion, your remaining motor output, and how far your networks have already reorganised.

Better targeting is not the same as better outcomes, and the review is direct about the difference. Neuronavigation improves the accuracy and reproducibility of where the coil sits, but it does not by itself control how far the stimulation spreads through the tissue, which depends on coil design, coil-to-cortex distance, intensity and your individual anatomy. And most of the clinical evidence supporting rTMS after stroke was gathered using conventional, non-navigated protocols. So its specific superiority over standard rTMS in stroke recovery has not yet been shown in controlled trials.

The authors call nrTMS a precision-enhancing tool rather than a treatment in its own right. rTMS in general is available in some UK centres for selected uses, but neuronavigated protocols for stroke rehabilitation remain specialised and investigational, held back by equipment cost, the need for recent MRI, planning time, operator training, and close teamwork between neurologists, physiotherapists and neurophysiology teams. Routine NHS use for stroke is some way off and depends on trials showing the added precision produces real functional gains. At ARNI, the ARNI Instructors and I work on the principle that any priming intervention only counts if the rehabilitation that follows is intensive and task-specific; nrTMS is worth following, but the training that comes after it is still what does the work.


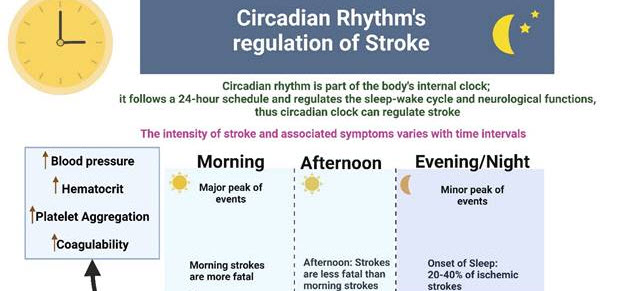
Did you know that strokes follow predictable time-of-day patterns? They happen more often in the morning hours and are often more severe near the end of the sleep period. A study published in the Journal of Clinical Investigation, led by Lauren Hablitz PhD at the University of Rochester Medicine and building on more than a decade of research by Maiken Nedergaard MD DMSc (whose lab discovered the glymphatic system in 2012), found that reinforcing the body’s natural daily rhythms after stroke improved motor recovery, shrank lesion size, lowered brain inflammation and boosted the brain’s waste-clearing system in mouse models. The benefits appeared even when treatment started three days after the stroke, well beyond the window for clot-busting drugs.

The glymphatic system circulates cerebrospinal fluid through brain tissue, clearing waste products and the inflammatory signals that build up after injury. This clearance is most active during sleep and controlled by the body’s internal 24-hour clock; stroke disrupts both, which slows the cleaning down when the brain needs it most. As Hablitz puts it: ‘stroke is not just a vascular event, but a disorder of timing.’ Her theory is that much of the lingering damage after stroke comes down to a failure of clearance: ‘if the system responsible for clearing signalling molecules isn’t working properly, everything builds up.’

The researchers tested four ways of restoring circadian rhythm: timed light exposure, melatonin, a clock-targeting drug called KL001, and time-restricted feeding (eating within a set daily window). KL001 and time-restricted feeding were then tested in stroke models, and both improved recovery, reduced lesion size and lowered inflammation. ‘All of the cytokines moved in the same direction,’ Hablitz notes… the brain appeared to be clearing inflammatory signals across the board rather than the treatment hitting one single target. Time-restricted feeding is already under study for heart disease and diabetes; it needs no specialist equipment and could, in principle, be done at home.

This is still animal research and human trials are needed before anyone can say it works the same way in people. Hablitz’s next steps are to establish whether improved glymphatic flow directly drives recovery and whether circadian-based interventions can move into clinical trials. At ARNI, the ARNI Instructors and I treat sleep and daily rhythm as rehabilitation factors rather than background lifestyle advice; this research sets out a neurological mechanism behind that.

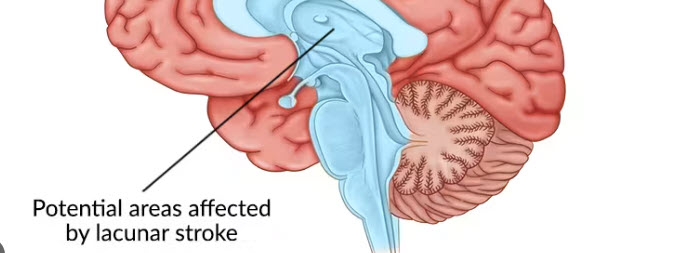
If you have had a lacunar stroke, you probably have been told it was caused by fatty plaque narrowing your arteries, and put on aspirin or another antiplatelet drug to prevent the next one. New research from the University of Edinburgh, published in the journal Circulation in July 2026, suggests that picture may be wrong; the strongest link was not with narrowed arteries at all, but with the widening and enlargement of the small blood vessels deep within the brain. This helps explain why the standard drugs you may be taking have often had limited success at preventing this particular kind of stroke.

Lacunar stroke happens when the brain’s tiniest blood vessels are damaged by a condition called small vessel disease. It is a major cause of disability and is linked to cognitive decline, dementia and a raised risk of further strokes; but until now, no one has been able to pin down exactly what drives it, which of course has made it hard to treat properly. To investigate, researchers from the University of Edinburgh, the UK Dementia Research Institute and international collaborators studied 229 people who had had either a lacunar stroke or a mild non-lacunar stroke. Each had clinical and cognitive assessments and MRI brain scans shortly after their stroke and again a year later, so the team could track the type of stroke, monitor the small vessel disease, and spot any new brain damage that developed over the year.

The results turned the usual assumption on its head. Narrowing of the larger arteries was not associated with lacunar stroke or with small vessel disease at all; it was more common in other forms of stroke, but it did not predict new brain damage on the follow-up scans. Artery widening was the opposite story. Patients with enlarged, widened arteries were more than four times more likely to have had a lacunar stroke… and the widening was also linked to more severe small vessel disease, faster progression of brain damage, and a greater chance of developing new ‘silent’ strokes… small areas of brain injury that happen without obvious symptoms. More than one in four participants developed these silent strokes during the study, even though they were taking the standard treatments meant to prevent them.

As Joanna Wardlaw, Professor of Applied Neuroimaging at the University of Edinburgh, puts it: ‘this study provides strong evidence that lacunar stroke is not caused by fatty blockage of larger arteries, but by disease of the small vessels within the brain itself… it explains why conventional treatments like antiplatelet drugs are not as effective for this type of stroke and highlights the urgent need to develop new therapies that target the underlying microvascular damage’. The point is not that aspirin is useless, but that for lacunar stroke it may have been aimed at the wrong target all along.

The research is already feeding into new treatment strategies. The LACunar Intervention Trial 3 (LACI-3) is testing whether existing medicines, including cilostazol and isosorbide mononitrate, can protect the brain’s small vessels, lower the risk of further strokes, and reduce long-term problems with memory, mobility and dementia after lacunar stroke. These drugs are already licensed for other uses, which could shorten the path to routine prescription if the trials succeed; but LACI-3 needs to report and be reviewed before anything changes in standard care, so realistic NHS use for lacunar stroke is still a few years away.

I’ve detailed Neubond on this Blog before – good news.. it’s on its way! As you know so well, after stroke, trying to move your affected hand and feeling nothing happen is one of the most frustrating experiences you can have… ut because the link between the brain’s intention to move and the sensory feedback that confirms movement has broken down.

Neubond, an Imperial College London spinout founded by Dr Patrick Sagastegui Alva, Jumpei Kashiwakura and Professor Dario Farina (head of Imperial’s Neuromechanics and Rehabilitation Technology lab, whose team spent over a decade developing the core science), has just announced a £1.5 million seed funding round led by Waseda University Ventures (its first investment in a UK company), alongside SFC Capital and New Wave Ventures, to finalise its wearable stroke rehabilitation platform and complete a pivotal clinical study at Charing Cross Hospital.

The device is basically a compact bracelet worn on the forearm. Sensors inside detect faint electrical signals from muscles even when the patient cannot see or feel any movement occurring; when the bracelet picks up a signal, a companion app shows the patient in real time that their muscle has activated, closing the sensory feedback loop that stroke has opened. As Professor Farina puts it: ‘we have strong evidence that neuroplasticity can be induced by detecting a motor command and applying artificial sensory feedback… guiding the brain to remake connections.’ The tech originated from prosthetic hand interface research; Sagastegui and Kashiwakura realised the detection component had an independent clinical application for stroke rehabilitation and built from there.

In a pilot with 15 patients, range of motion improved by 30% after one month. These are early numbers from a small sample; the Charing Cross study will provide the larger dataset needed to inform a full clinical trial and MHRA approval. The funding also completes product development toward a device that can be used at home independently and monitored remotely by clinicians… which addresses one of the most persistent gaps in stroke rehab: what continues (or more commonly does not continue) after hospital discharge. Co-founder Kashiwakura is direct about the aim: ‘motivation is vital for stroke patients; our platform uses a simple biofeedback mechanism so that patients can see the effect their rehabilitation efforts are having.’

Neubond is of course not yet available and MHRA approval is still ahead; routine availability is realistically several years away.

If your affected hand still doesn’t feel & function right, or your arm still isn’t doing what you ask of it months or years after stroke, this summary of research published in Nature Medicine on 26 June 2026 may be worth a read so you know about a future tech intervention that could help. So, researchers at the Medical University of Vienna and ETH Zurich, led by Professor Stanisa Raspopovic at the Centre for Medical Physics and Biomedical Engineering, have developed a rehabilitation platform called MultiSensy that combines immersive virtual reality with transcutaneous electrical nerve stimulation; in a randomised feasibility trial with 34 chronic stroke patients, the system produced nearly twice the upper limb motor improvement of conventional rehabilitation over the same three-week period.

You wear a VR headset and perform goal-oriented tasks in a digital environment (reaching for objects, grasping, pinching, rotating the forearm) designed around occupational therapy principles and adapted to your specific level of impairment. At exactly the same moment, electrodes placed on the skin of your affected arm stimulate the peripheral nerves in real time, so that when your hand touches a virtual object in the headset, you actually feel something in your hand simultaneously. The stim targets the median nerve, which runs from the forearm into the hand and is responsible for sensation in the thumb, index finger, middle finger and part of the ring finger…the fingers most involved in functional grip. Each session begins with a ten-minute calibration of the electrical stimulation to each participant’s individual sensory threshold; the difficulty of the virtual tasks then adjusts based on performance.

So in this therapy, the brain receives a congruent signal from both the motor and sensory systems simultaneously, which is what normal functional movement requires…On the Fugl-Meyer Assessment for the upper limb – the clinical gold standard for measuring post-stroke upper limb motor impairment – the MultiSensy group showed nearly twice the improvement of the conventional rehabilitation control group across 12 sessions over three weeks. Similar advantages appeared on the Action Research Arm Test, which measures real functional arm and hand use in daily tasks. Participants also showed improvements in touch sensation and in their perception of their affected arm; after stroke, some survivors struggle to feel touch in the affected hand and may perceive the arm as distorted in size, shape or position (a phenomenon known as altered body representation) something conventional rehab rarely addresses.

As lead author Valerio Aurucci of ETH Zurich puts it: ‘after a stroke, patients often have difficulty not only moving the affected limb, but also feeling it and perceiving it correctly; MultiSensy was developed to reconnect movement, sensation and body awareness during rehabilitation.’The platform logs precise movement and trajectory data automatically throughout every session, giving clinicians objective performance indicators to monitor recovery and adapt therapy over time rather than relying solely on periodic clinical assessments. The researchers flag this as particularly relevant to a potential home-based model, reducing dependence on clinic attendance for people in the chronic phase of stroke recovery who may have limited access to intensive rehabilitation.

MultiSensy is still at the research stage.. no UK clinical trial is registered and no NHS adoption pathway has been announced. Routine NHS availability before the early 2030s is unlikely. At ARNI, the ARNI Instructors and I work on sensation, perception and movement together from the earliest stages of upper limb rehabilitation; training grip and reaching while simultaneously feeding the hand a real sensory signal is consistent with what we know about how the brain relearns movement after stroke, and MultiSensy seems one of the most technically coherent attempts to build that into a scalable clinical platform I’ve heard about for a while.

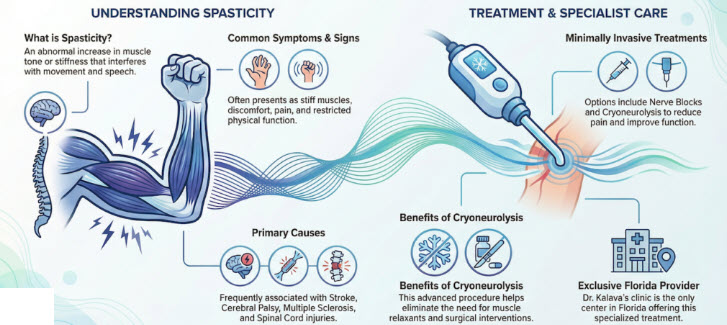
BOTOX never did much for your spasticity? Or never worked as well as you hoped? Now there is a longer-lasting NHS-available alternative that a number of ARNI survivors have tried and rated positively. Cryoneurolysis has been used in medicine since the 1970s for sensory pain management; in 2018 researchers adapted it to target the motor nerves driving spasticity specifically, and by January 2024 Oxford University Hospitals NHS Foundation Trust had established a routine cryoneurolysis service at the Oxford Centre for Enablement, accepting GP and consultant referrals from anywhere in the UK. Botulinum toxin has a dose ceiling, a duration limit of around 3 months, and can develop tachyphylaxis, diminishing response with repeated injections over time; cryoneurolysis has none of those constraints, and its duration of effect of 6 to 12 months from a single treatment is one of its most practical advantages.

The procedure uses a handheld probe to freeze targeted nerve fibres to around -88°C, temporarily halting the signals driving spasticity while leaving the endoneurium, the nerve’s structure, intact; natural regeneration follows over 6 to 9 months. A diagnostic nerve block with local anaesthetic is performed first; if your muscle relaxes and passive mobility improves, you’re confirmed as a candidate, and the cryoprobe is then guided to the precise motor nerve using ultrasound and electrical stimulation so surrounding tissue is unaffected.

The positive evidence for the intervention seems to building quite consistently, but is still primarily case series rather than large-scale RCTs. For example, a feasibility case series published in Neurology International in April 2026, treating three adults with chronic post-stroke hemiparesis, found MAS scores decreased by at least 2 points in targeted patterns with improvements sustained at 6 months and no serious adverse events. A larger 2025 study of 59 participants with plateaued or refractory upper limb spasticity found significant improvements at 12 months in shoulder abduction (+9.7°), shoulder flexion (+8.1°) and elbow extension (+21.3°), alongside MAS reductions of 2.0 points for shoulder abduction and 1.7 for shoulder flexion… average daily pain, participant satisfaction and upper limb disability all improved. A January 2026 case in Neurology International documented a stroke survivor 12 years post-injury with an implanted FES device; targeted sequential cryoneurolysis improved his gait deviation index beyond minimal detectable difference thresholds – confirming for the first time that cryoneurolysis is fully compatible with implanted FES devices.

In Luxembourg, the spastiCRYO-LL trial received ethics committee approval in April 2024 and is generating the first quantitative gait-laboratory evidence for cryoneurolysis at scale. In Canada, a mechanistic pilot study at Parkwood Institute is targeting 25 stroke patients to characterise neuroplasticity effects via TMS, fMRI and near-infrared spectroscopy – testing whether the controlled nerve disruption cryoneurolysis creates may itself trigger neuroplastic reorganisation beyond simple tone reduction. In the UK it’s available at Oxford University Hospitals, the National Hospital for Neurology and Neurosurgery at Queen Square (UCLH) and St George’s University Hospitals. Your GP, stroke physician or neurologist must submit a formal referral.

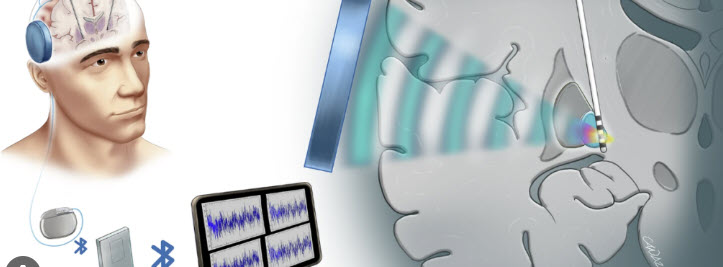
What if sound waves could help your brain reconnect after stroke? Well, if your gait control is still bad, your coordination unreliable and or your arm not doing what you ask of it, the reason (as you know) is almost always because the cortical networks that once coordinated those movements have been disrupted, and the brain is struggling to reroute communication across damaged circuits. But maybe low-intensity transcranial ultrasound stimulation (TUS) could be the next ‘big thing’ after FES?

Interesting to read a study just published in the Journal of Neuroscience, led by Yi Yuan at Yanshan University, which used low-intensity transcranial ultrasound stimulation (TUS) in a mouse model of ischaemic stroke over one week and found that TUS improved gait and restored communication between cortical brain networks, with those network improvements directly linked to measurable behavioural gains. What makes this study notable beyond the results is that it begins to explain the mechanism not just how TUS works on motor function after stroke, but how; by restoring cortical network connectivity in the damaged area, it allows the brain to resume the inter-regional communication that coordinated movement requires.

TUS delivers focused sound waves through the skull to targeted brain regions without electrodes, implants, surgery or drugs. The skull is no barrier; low-intensity ultrasound passes through it and reaches the target area directly, which gives TUS greater spatial precision and deeper reach than transcranial magnetic stimulation or transcranial direct current stimulation. A systematic review covering 5 human studies and 13 animal studies found TUS effective in supporting stroke recovery, particularly motor function; and a phase one trial published in the Journal of NeuroEngineering and Rehabilitation in March 2026, recruiting ten subacute stroke patients, demonstrated safety and preliminary efficacy of focused TUS for upper limb motor recovery.

For stroke survivors with persistent motor difficulties, the mechanism TUS targets is directly relevant to what rehabilitation is also trying to achieve. Coordinated movement depends not on any single brain area but on communication between multiple cortical regions working in sequence; stroke disrupts those sequences at the network level, which is why motor recovery can plateau even when a survivor is working hard in rehabilitation. A technology that restores inter-regional cortical communication rather than simply stimulating peripheral muscles or applying broad electrical fields addresses the problem closer to its source, and research published in 2024 has also shown that very low-intensity ultrasound facilitates glymphatic clearance in the brain, connecting TUS to the same waste-clearing system whose role in stroke recovery has been highlighted by recent circadian rhythm research.

Realistically, routine clinical availability is several years away;  larger randomised controlled trials are needed and optimal stimulation parameters (frequency, intensity, duration and target site) are still being established across different stroke presentations.. At ARNI, the ARNI Instructors and I work on motor coordination, gait and upper limb function from the earliest stages of rehabilitation; and so a brain-level intervention that restores cortical network connectivity alongside intensive rehabilitation rather than instead of it is exactly the kind of adjunct that could extend rehab optimally…

Researchers at Duke University School of Medicine have published findings in Nature describing a technology called LinCx that may have direct relevance to stroke survivors.The basic idea is this: if a brain connection is damaged, instead of trying to fix it or medicate around it, you build a new electrical path between the neurons that need to talk to each other. Like dealing with a road closure, LinCx creates a working detour with a biological ‘wire” designed to bypass broken or disrupted brain connections.

Stroke frequently does not kill every neuron in the affected area; what it does in many cases is sever the connections between neurons that remain alive and present. Those disconnected cells can no longer communicate reliably – and it is that loss of communication, rather than simple cell death, that also underlies persisting problems after stroke: like fatigue, low mood, cognitive difficulty etc. LinCx, led by Kafui Dzirasa at Duke, does not attempt to repair damaged synapses; instead it builds a new electrical ‘bypass’ between specific neurons, restoring signal transmission without altering the brain’s existing connections.

The system uses proteins originally identified in fish, where they function naturally as electrical synapses. The Duke team engineered these proteins to bond only with matching modified partners, preventing interaction with the brain’s natural proteins and avoiding unintended connections elsewhere. Earlier attempts to exploit electrical synapses in research settings frequently produced connections in unintended locations; LinCx addresses this through a lock and key mechanism in which each engineered protein recognises only its designated partner. Where current treatments – antiepileptic drugs, antidepressants, electrical stimulation devices – act across broad areas of neural tissue, LinCx targets selected neurons only. In animal testing, the added connections strengthened communication in specific circuits, altered brain-wide activity patterns, and produced measurable behavioural changes related to stress responses and social interaction across two different species.

The implications for stroke survivors are worth considering: post-stroke epilepsy, affecting approximately one in ten survivors, arises from disordered electrical activity in damaged circuits; current treatment suppresses symptoms pharmacologically without addressing the underlying disruption. Post-stroke depression, which affects around a third of survivors, involves significant circuit level dysfunction in the connections between the prefrontal cortex and subcortical mood regulation structures – connections that medication restores only partially. Cognitive impairment, spasticity and post-stroke fatigue similarly reflect disrupted circuit communication rather than simply lost tissue; and in each case a technology capable of restoring specific connections rather than broadly modulating the nervous system.

LinCx remains at the animal research stage. Dzirasa has indicated that the next step is establishing whether the technology can override synaptic deficits caused by lifelong genetic disruptions – still considerably short of human trials. The UK regulatory pathway through the MHRA, encompassing safety, tolerability and efficacy phases, typically requires ten to twenty years for a novel biological technology. The research is funded by the Howard Hughes Medical Institute, the National Institutes of Health, the Burroughs Wellcome Fund and the Hartwell Foundation. Routine NHS availability before the late 2030s is unlikely; the 2040s is a more grounded estimate.

A blood test designed to identify large vessel occlusion stroke in the back of an ambulance has received UKCA marking and is now being deployed with London Ambulance Service. Large vessel occlusion, or LVO, is the most severe form of ischaemic stroke; it occurs when a major artery supplying the brain is blocked by a large clot, and the only effective treatment is mechanical thrombectomy. Paramedics really have had no reliable way of identifying LVO in the field; so patients have to therefore be taken to the nearest hospital rather than the nearest thrombectomy centre, losing time that can’t be recovered. LVOne, developed by Upfront Diagnostics over eight years with support from the University of Cambridge, Newcastle University, Innovate UK and the National Institute for Health and Care Research, is designed to help close that gap.

The test works from a finger-prick blood sample and delivers results in under ten minutes, measuring two biomarkers: D-dimer, associated with clot formation, and GFAP, associated with bleeding in the brain. The first deployment equips approximately 280 London Ambulance Service vehicles covering a population of roughly 6.5 million people; paramedics will combine LVOne with existing assessment tools to determine whether patients should go directly to one of London’s Hyper Acute Stroke Units. The programme is led by ARNI supporter and kind (past) presenter on ARNI courses, Dr Robert Simister, who is a consultant neurologist at the National Hospital for Neurology and Neurosurgery at UCLH. Brain tissue dies at approximately 1.9 million neurons per minute in LVO stroke; getting the right patients to the right hospital faster directly reduces the severity of the damage that rehabilitation then has to address. Given that LVOne is already in active NHS use, wider national rollout within two to three years is plausible if the London pilot data supports it.

Mechanical thrombectomy has rapidly become one of the most effective interventions of ALL in stroke, when performed quickly; studies consistently show that for every hour of delay, the chance of a good outcome falls by roughly 20 per cent. Yet across the UK, access remains uneven – provision outside major urban centres is limited, and many patients who would benefit never receive it at all. LVOne does not solve the access problem on its own, but accurate prehospital identification of LVO is a necessary precondition for any serious improvement in thrombectomy rates; you cannot route patients to the right centre if you don’t know which patients need to go there. The UKCA marking also means that other ambulance services across the UK can now adopt the test without waiting for further regulatory approval – and pressure from us in the stroke community for that to happen quickly is probably entirely justified!

ARNI Stroke Rehab & Recovery says: this is one of the most practically significant developments in prehospital stroke care in years, with real potential to get patients to the right treatment faster than anything previously available in the field; and the case for rapid national rollout beyond London is really strong.


We are on Facebook

ARNI